
TL;DR

Turn your wind-down time into listening time
- Thousands of audiobooks, podcasts and originals
- Listen on your phone, tablet or Echo — also offline
- Cancel anytime
An Athletech News report says obesity medications can support meaningful weight loss, but treatment should also address muscle, fitness and everyday function. It calls for resistance and aerobic exercise, nutrition support and qualified exercise professionals to be integrated into care. The report does not provide new trial results or a formal clinical guideline.
An Athletech News report argues that obesity medication care should pair drugs with exercise, nutrition and behavioral support, rather than measure progress only by pounds lost. The report says resistance training, aerobic activity and adequate protein can support strength, fitness and physical function during significant weight loss, while acknowledging that some loss of lean body mass can occur.
The report describes GLP-1-based and other obesity medications as an important development in obesity care, citing clinical trials that have shown meaningful weight loss and improvements in metabolic health. It says much of the public discussion has focused on eligibility, cost and insurance coverage, with less attention paid to how the body changes during weight loss and how to support health beyond the scale.
It notes that significant weight loss, regardless of how it is achieved, typically reduces both fat mass and lean body mass. Fat loss makes up most of the weight reduction, the report says, but some muscle loss can occur. Because skeletal muscle supports strength, mobility, metabolic health and daily activities, the report argues that maintaining muscle and strength should be part of treatment planning.
The report recommends including resistance exercise to help preserve or build strength, alongside aerobic activity to support cardiorespiratory fitness and cardiovascular and metabolic health. It also identifies adequate dietary protein as a potential support for lean tissue. These are presented as components of a comprehensive approach, not as substitutes for prescribed medication or individualized medical care.
Beyond the Number on the Scale
Focusing only on weight can leave important aspects of health unmeasured. The report says fitness, strength, metabolic health, physical function and quality of life also matter when judging whether treatment is helping. It describes higher fitness and strength as independently associated with lower risks of chronic disease and premature death, while offering no new data or specific risk estimates in the supplied material.
For patients and clinicians, the practical point is that medication-related weight loss does not automatically deliver every desired health outcome. A treatment plan that also considers muscle, mobility and sustainable habits may better address how a person feels and functions over time. The report frames this as an opportunity to build lasting behaviors while medication helps support weight reduction.
That approach also has implications for care delivery. The report calls for stronger links among prescribers, registered dietitian nutritionists and qualified exercise professionals. It says clear credentials and scope of practice can help clinicians make appropriate referrals and give patients confidence in the professionals guiding physical activity.
Products Worth Considering

BowFlex Results Series SelectTech 552 Adjustable Dumbbell
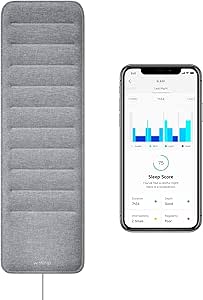
Withings Sleep Under-Mattress Sleep Tracking Pad

Garmin Venu 3 Fitness Smartwatch, 45 mm, Black
As an affiliate, we earn on qualifying purchases.
Medication Within Broader Obesity Care
The source describes obesity as a complex, chronic disease shaped by biology, environment, behavior and social factors. It presents medications and lifestyle changes as complementary approaches, rather than competing choices. The article’s central argument is that drugs may reduce appetite, increase satiety and support weight loss, but do not themselves build muscle or improve cardiorespiratory fitness.
The report also addresses public discussion about lean body mass changes among people taking obesity medications. Its broader point is that some muscle loss can accompany substantial weight loss generally; the supplied material does not establish that this effect is unique to a particular drug or quantify how much muscle patients may lose. It cites a related column by the author in U.S. News & World Report, but provides no study details or clinical recommendations beyond the strategies described.
For exercise referrals, the report points to the U.S. Registry of Exercise Professionals, supported by the Coalition for the Registration of Exercise Professionals, as a resource for checking credentials. It also says the American Council on Exercise is preparing professionals to work with physicians and other health providers. These details reflect the report’s call for professional coordination, not a claim that every health system has adopted such a model.
“Long-term health depends on much more than the number on the scale.”
— Athletech News report
Evidence and Implementation Questions
The supplied report does not give the publication date, identify specific clinical trials, quantify muscle changes or compare outcomes among different medications, exercise programs or protein targets. It also does not set out a standardized exercise prescription or specify how much protein an individual should consume. Those details should not be inferred from its general recommendations.
It remains unclear how widely health systems currently include qualified exercise professionals in obesity treatment, how referrals are funded, and whether patients have access to those services. The report advocates credentialed support but does not provide data on availability, cost or patient outcomes from such programs. Individual exercise and nutrition plans may also need to account for a person’s health status and abilities; medication or lifestyle decisions should be discussed with qualified health professionals.
Integrating Support Into Care
The report’s proposed next step is for healthcare systems to make exercise, nutrition and behavioral support routine parts of obesity care and build clearer referral pathways to qualified professionals. Clinicians can use credential registries and established scopes of practice when identifying exercise specialists, while coordinating with dietitians and other members of a care team.
The source does not announce a policy change, new program or implementation deadline. Whether its recommendations lead to broader adoption will depend on health-system decisions, professional coordination and patient access. The report’s stated direction is to judge progress through more than weight alone, including strength, fitness and everyday function.
Key Questions
Does the report say obesity medications are ineffective on their own?
No. It says clinical trials have shown meaningful weight loss and metabolic improvements. Its argument is that medication does not replace exercise, nutrition or other support for broader and longer-term health goals.
Why does the report emphasize muscle during weight loss?
It says significant weight loss typically includes reductions in both fat mass and lean body mass. Muscle supports strength, mobility and everyday function, so the report recommends considering ways to preserve strength during treatment.
What kinds of activity does it recommend?
The report identifies resistance exercise for strength and muscle support, and aerobic activity for cardiorespiratory fitness and cardiovascular and metabolic health. It does not provide a one-size-fits-all schedule or exercise prescription.
Does the source provide a specific protein target?
No. It says adequate dietary protein can support lean tissue but gives no amount or individualized nutrition guidance. Patients should discuss dietary needs with an appropriate health professional.
Source: rss







